
Léopold Busquet
‘All disturbances in the body should be considered in terms of the logic of its function.’
Today I want to discuss a painful subject — the TMJ. I will not tell you fairy tales, only facts from my practical work, information from conferences and some scientific publications. I will try to be understandable and not overload you with terms, diagnoses and so on. More and more patients come to me after going through a thousand circles of hell with different specialists, having examinations from their feet to the crown of their head, taking many expensive medicines that, if they bring relief, do so only for a while.
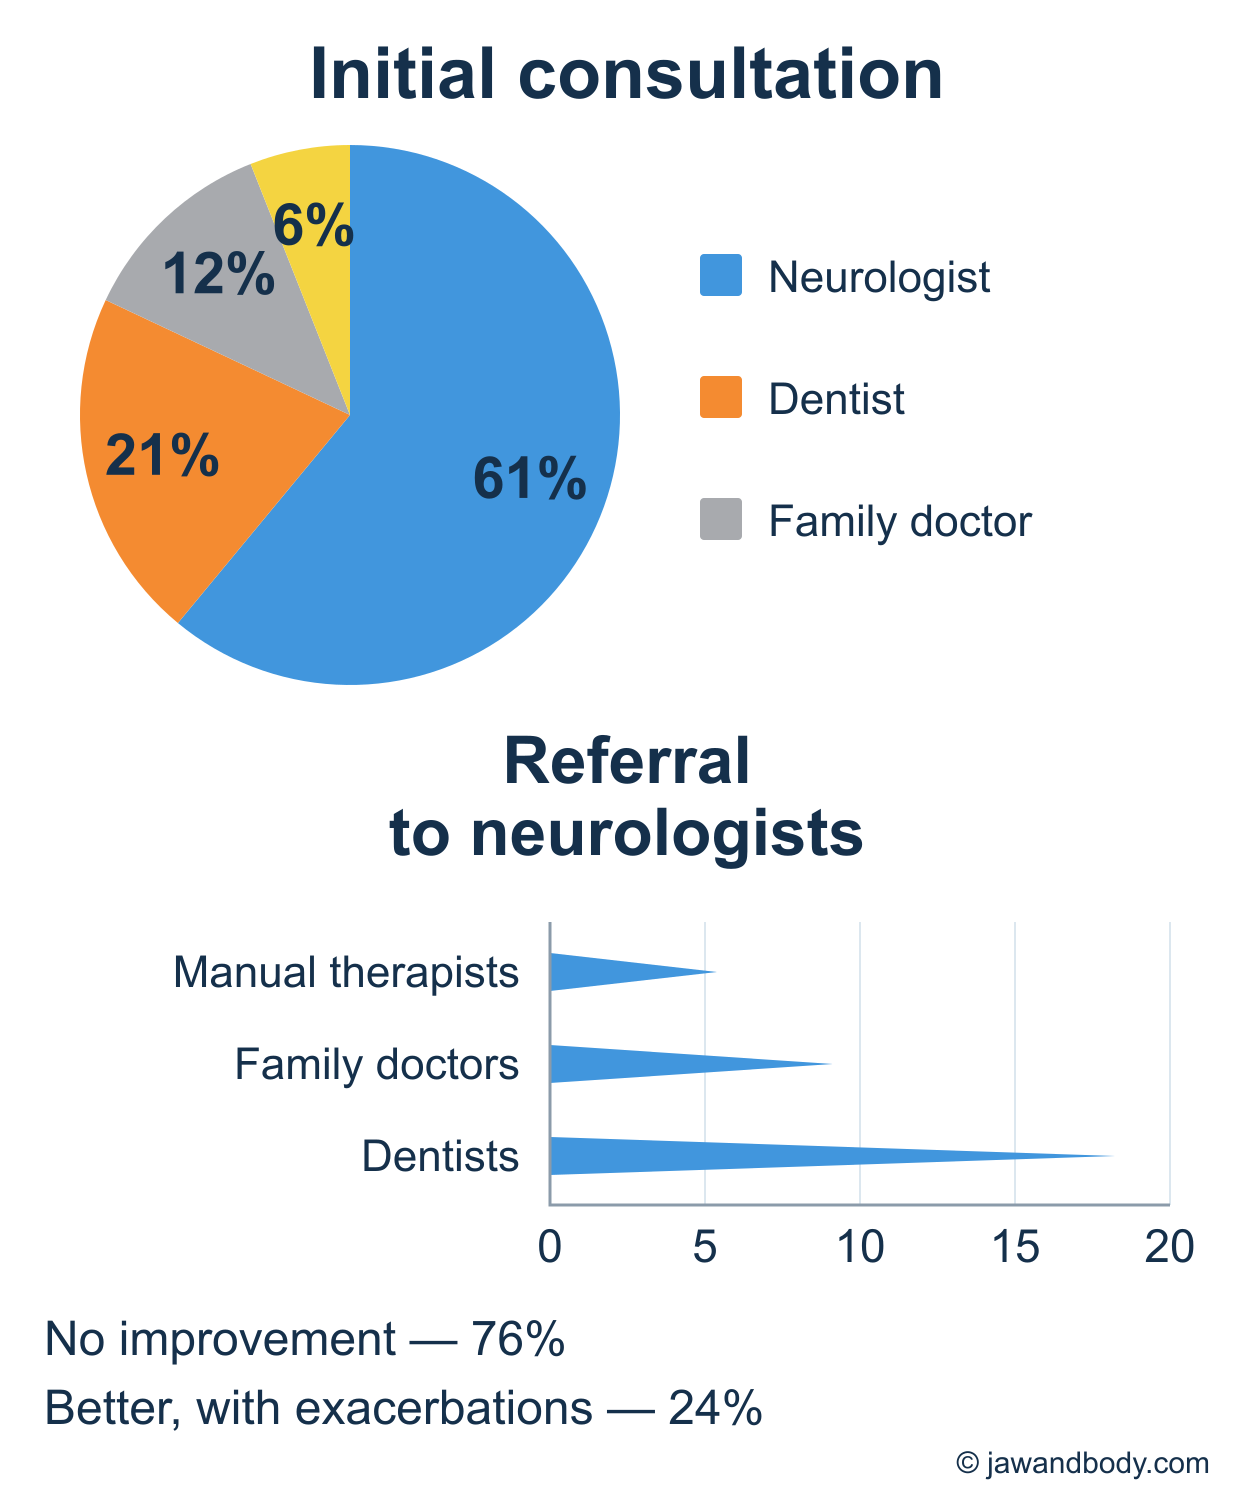
Although these are my observations from Ukraine, I think it is like this everywhere. In our world, chasing money, we forget we will not take it into the next world. Alas, many neurologists do not even want to refer patients with aching pain and shooting pains around the face, ear, eyes, back of the head and so on. During a flare-up these can drive you mad: they become sharp and continuous, and you simply want to tear off a piece of your head and throw it away. Neuritis/neuralgia/paresis/paralysis — almost everyone arrives with a diagnosis on a piece of paper, and behind them are many bottles of IV infusions, pills, not days but even years in hospital, and money. Had your infusion — seems better, goodbye, see you in six months. Doctor, why is this happening? Well, your nerve is inflamed, and how they love to fill your head with this: oh, now it will keep getting inflamed like that; you probably caught a chill in a car or minibus somewhere. Indeed, why investigate and refer a ‘bag of money’ that will bring you money every six months? Come to your senses: we are talking about health!!! The other side: look at the figures for dentists. Yes, 90% say, oh, you need a neurologist, this is not our concern. Of course, they simply do not even know that a crown/filling/prosthesis they have fitted incorrectly will cause that same neuritis/neuralgia.
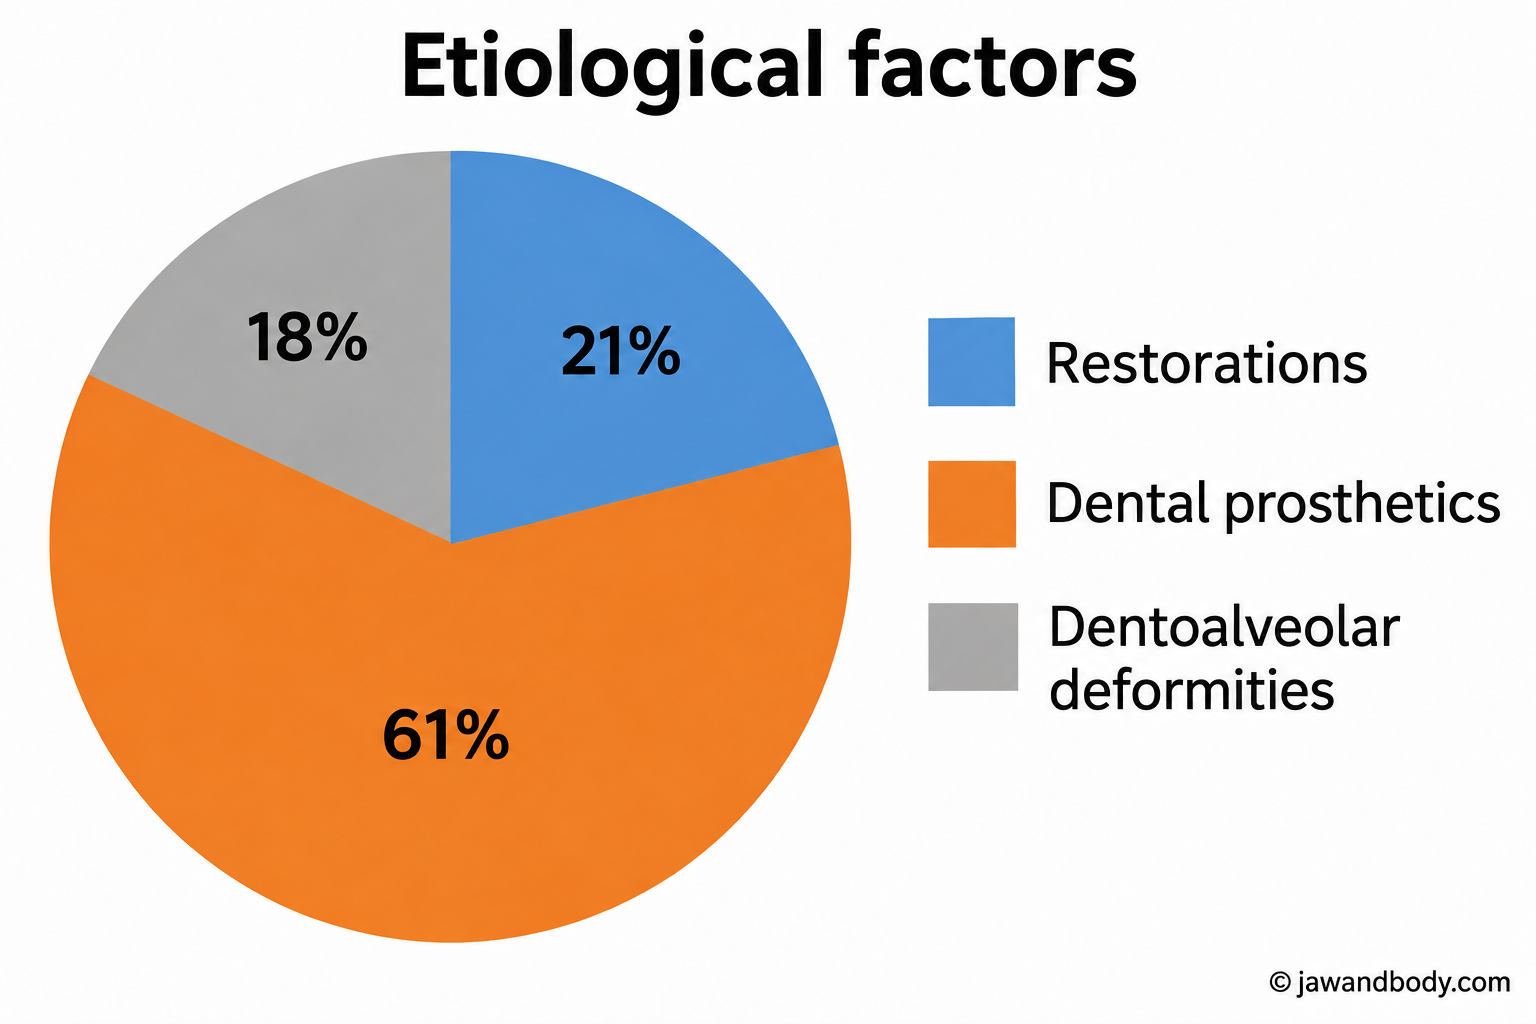
So when do patients finally arrive? Option 1: ‘smart patients’. After dozens of bottles of IV infusions and packets of pills, they sit reading the internet, intuitively opening and closing their mouths and touching their faces, trying to understand where it hurts most. Oh, Eureka, that sounds like me too! That is when they come to me, while it can still be corrected. Option 2: patients who fully trust our specialists, our scientific luminaries. A sad outcome: the disc has worn away and cannot be corrected.
Let us work out why it happens that seemingly it is the nerves, yet you need a dentist. It seems strange, because everyone is used to thinking a dentist means teeth and nothing else.

Look at where this branch of the trigeminal nerve runs, marked by the red arrow. Accordingly, if the jaw shifts slightly backward or sideways, it compresses that branch, and affecting one branch means exciting the whole nerve under the laws of physiology. This is where the concept of radiating pain comes from. It can radiate anywhere throughout the head. Treat the nerve as much as you like (symptomatic treatment), but without removing the cause there will be no result. You will not necessarily feel the jaw shifting into an incorrect position. Alas, you will feel it when your jaw becomes crooked and clicking and crunching begin. Even after removing the dental cause, there are a couple of factors: muscle memory, and tension in one muscle causing tension in all the others as the body compensates to align its position.

Here is a clear example: I show what happens to the neck muscles with disturbances in the dentofacial system, sitting and standing.

Electromyography data are available.
A clear illustration of where pain can radiate, and the answer regarding frequent migraines and their treatment.

Temporomandibular Joint Dysfunction — One of the Causes of Stroke
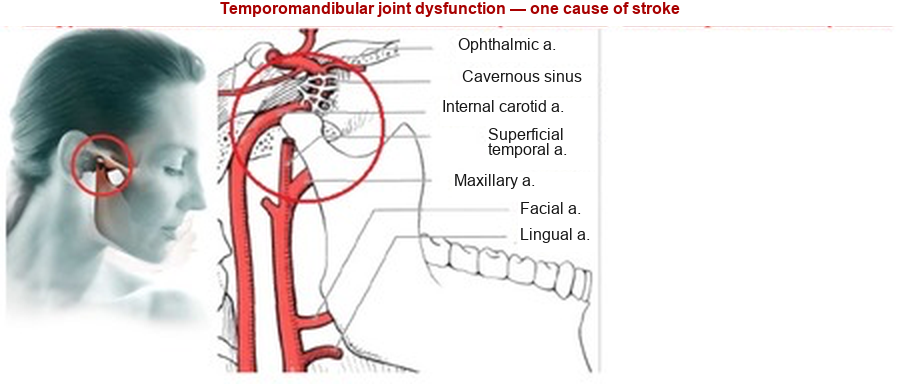
Look carefully at this picture, at where the carotid artery is. This is what else a backward shift of the jaw can lead to. It is also not our whim to restore fully with bridges or crowns, or fit removable dentures!!! with adequate height (because reducing height on dentures again pushes the jaw backward)!!! Now the excuse ‘well, it clicks, so it clicks, and it does not stop me living’ does not sound so good, does it?
Impaired patency of the internal carotid artery is explained by a disc–neurovascular conflict: irritation of the artery’s perivascular nerve-receptor apparatus due to periodic or constant dislocation of the intra-articular TMJ disc during jaw clenching, with simultaneous stretching of the TMJ capsule into a bulge. Initially, this causes local vascular spasm, followed by gradual recalibration of the vessel until it is completely compressed.

It is important to note that the enormous plasticity and development of carotid artery collaterals (natural anastomoses) often allow the body to compensate, for a time, even for complete blockage of the internal carotid artery at the entrance to the skull (the compensation stage). But with increased physical and emotional loads and exhaustion of compensatory mechanisms with age, a breakdown occurs (the decompensation stage), bringing catastrophic consequences: senile dementia, stroke, and a fatal, sometimes sudden, outcome. Guys, these are not fairy tales: I can provide plenty of SCIENTIFIC evidence from various scientists and many references to foreign authors.
What about Orthocraniodontics?
Why is there no guarantee? Because everything depends on the depth of dysfunction and instability of the entire body. Moreover, without a competent osteopath, in a profound disturbance of postural balance you cannot consolidate the result or achieve it to the desired extent. Without untangling the knots of overload, success is rather difficult: the body needs help, a push.
Can we make things worse? No, because this appliance is guiding, not rigid. It does not have enough force to pull or over-pull all the components of the skull.
Tighten up the bite with braces afterwards? Absolutely not. Destroy what we have achieved? I ask orthodontists who will say ‘what is wrong with that?’ to send me a TRG in frontal projection plus an orthopantomogram before and after treatment.
The ALF Appliance, or Pain Is Measured in Microns
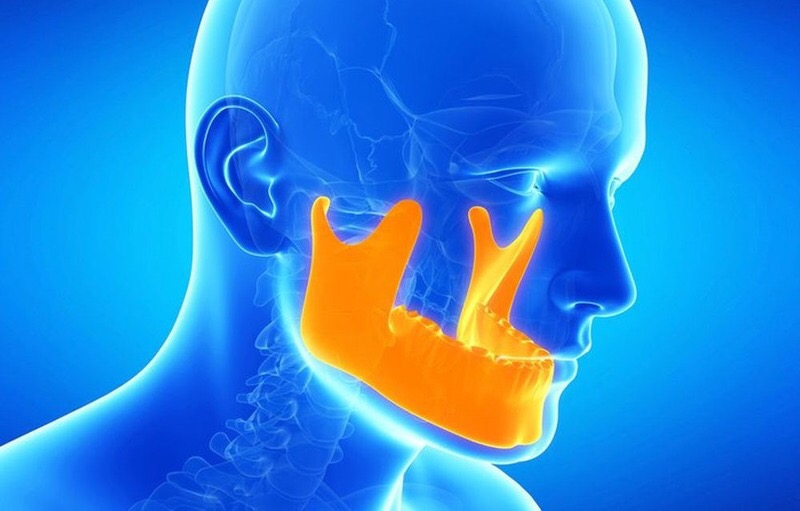
Disturbances in the sphenobasilar synchondrosis system — that is the root of the evil. When the front of the skull shifts one way and the back the other, life will clearly be no fairy tale. These hooks attach to the upper jaw, so acting on it with the right approach is the key to success.

Muscles responsible for moving the lower jaw also attach to this bone. And do not forget that this is the cranial base, with many openings through which that unfortunate trigeminal nerve also passes.


Yet initially, a couple of years ago when I began, I too was sceptical. However, there are changes, and there is also the patient’s well-being when you simply bring them back to life.
Take care of yourselves.
Respectfully, Viktoria Viktorovna Vovk.
viktorija.viktorovna.vovk@gmail.com


3 comments
Ask a careful question or add useful context. New comments are reviewed before publication.